

Thinkboi the only funny + non-jargon healthcare newsletter: https://xitter.twitterapi.xyz/t.co/61zgESgkhw learn healthcare quickly with crash courses: https://xitter.twitterapi.xyz/t.co/C6cWc5YHK7
New York
Joined September 2013
- Tweets55K
- Following1.2K
- Followers67.1K
- Likes31.3K





Pinned Tweet
I’m really excited to announce something months in the making…announcing a 5 week hackathon with $250K+ in total grants and prizes!!!
Build @ Deerfield (powered by Out-Of-Pocket) is for early stage teams that want a chance at non-dilutive capital, support in building their projects, and a stage to present what they’ve built.
You can see more details below, but in general Deerfield Management and Out-Of-Pocket are joining forces to do something big for the New York healthcare community.
We’re selecting 12-15 teams who want to build for 5 weeks. You’ll get some cash upfront to start, mentors you can access during the build-time, and then a pitch showcase and reception with the broader New York healthcare community on January 20-21, 2027 at Cure in NYC.
Judges at the showcase will pick a few winning teams to receive additional grants and prizes to continue their work. And we’ll have a really good time 🙂

2
25
9,694
Considering how much concern there is around the distribution and governance of AI, I’m kind of surprised there wasn’t this level of discourse around short form video which arguably feels as harmful (but just has way less extinction risk)
2
9
1,582

I was surprised at how much Medicare/Medicaid/Social Security are now propping up local economies and personal incomes
If you look through the data, Medicare/Medicaid have become the biggest sources of income for particularly non-metropolitan areas. Some stats in the data:
- Government transfers are now 17.6% of all personal income in the US, up from about 8% in 1970. Medicare and Medicaid are 46% of all government transfer dollars!
- 53% of counties get more than 25%+ of their income from government transfers (this covers about 72M people).
- Kentucky seems to be the home of the Colonel and government transfer programs. Twelve of the top fifteen counties receiving government transfers are there. Owsley County gets 63% of personal income from transfers, and Medicaid alone is 32% of all income in the county.
Those government transfers via Medicaid/Medicare get transmuted alchemically into jobs. Phoebe Putney Health System has 6000+ workers and is the largest employer in southwest Georgia. Dougherty County, where it's based, gets 34% of its personal income from government transfers.
In New York we have a program that pays friends and family as caregivers. In 2023 it grew by 57,000 jobs and became 38% of all job growth in the state (they’ve made changes to the program now that have flattened it).
We have become a country of healthcare jobs with a propping of government dollars. Is that fine?
I think this grand bargain worked for a while. We were still seeing economic productivity, government spending hadn’t yet gotten too crazy, etc. But a few things are happening now that suggest the bargain is falling apart.

EIG report here (where the data comes from: eig.org/great-transfermation…
my longer writeup of the Healthcare Jobs Program and why it's teetering: outofpocket.health/p/healthc…

in the last post we talked aboutabout AI models for neurodivergent people.
Here's one person that texted me their experience with Instinct.
In the newsletter, Brody Clemmer made an excellent case around how LLM outputs today can be difficult for people who are neurodivergent to process and act on.
And instead an interesting product/company idea might be experimenting with how information is delivered modified for that end user (e.g. changing the cadence/information density in responses, using multi-modal outputs, etc.)

Feels like there's something there - full idea + writeup here: outofpocket.health/p/more-he…

maybe GLP-1s will be the bitter lesson applied to life sciences as we start learning more about how it lives upstream of even more diseases than we think
Less than a week left to apply to our hackathon with Deerfield Management, where we're giving grants and cash prizes for people to start healthcare companies
We're especially interested in people that want to start companies in biosecurity, hardware/robotics, drug discovery, and private data exhaust

New essay - healthcare jobs are basically keeping the US labor market afloat, but it's starting to see some weakness. This raises questions about how local economies are going to prepare.
There are three big factors I see:
1) The government is now cracking down on how money is getting pumped into states. I took a look at the data and governmental transfers to states via Medicare/Medicaid are now an enormous amount of dollars in that economy. What happens when that gets shut off?
2) Local politicians are starting to realize that the healthcare jobs program is actually causing non-healthcare jobs to avoid the state. Indiana provides an interesting example here.
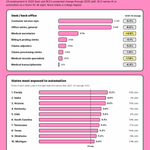
3) AI is going to hollow out many admin jobs. I sliced the BLS data which actually flags which jobs are at risk for automation. It also presents an issue where full automation will extract dollars from these economies and concentrate them where the AI companies are based (e.g. SF, NY, etc.).

full essay is here + how I think we need to create a new jobs program (and a suggestion on what that could be)
outofpocket.health/p/healthc…

1
1
376
lol @plainyogurt21 sent this kinda out there idea - crowdsourced “drug vibes” from conferences
"Currently we have expensive KOL services that pay doctors 800$ per call to get a vibe on new drugs.
I propose we get med students at Conferences to wear a mic while at the conferences and track all the audio said for $800. Have conferences -> see the insights -> sell the data to Neolabs.
We also get live reactions to new drug results and where the real unmet needs are.
EXTREMELY useful information to docs, to biotechs and ultimately probably worth a few $M to Neolabs. KOL insights are hard to get, expensive, and opaque.
LLMs enable use to process ALL this audio without issues. All we do is find a med student willing to wear a mic for a weekend in a one party consent state"

Tomorrow's post: Healthcare is a US jobs program that is now wobbling
It's been interesting to watch the job reports over the years and see that healthcare is basically propping up the entire labor economy
But there are a few things happening now that seem to be threatening this, which then raises the question about what's going to happen to local economies that are currently afloat because of healthcare

sign up to get it - would love to have a discussion with people that have ideas on what the next jobs program can look like
outofpocket.health

2
2
1,791
We need a new method of teaching post AI
IMO people are worried about AI eroding critical thinking because it's being mapped to previous methods of teaching (memorization, lectures, recall, etc.)
But maybe AI also creates opportunity for new and maybe better methods of learning
Multiplayer learning - right now so much of learning revolves around students do things solo (reading, papers, tests). The next wave should be multiplayer - for example use AI to prep and you debate in class.
Ambiguous exploration - give people some environment or general end goal (e.g. sell something for $1 on the internet, or here's a virtual sim environment where you can tweak variables/explore and report back your findings
Grading the process vs. outcome - The current form of testing/grading is based on the idea that there are a fixed amount that the people teaching can grade. Maybe now instead you can grade based on the process instead (e.g. what kinds of things you tried and explored)
An interesting litmus test for how AI might change specialties - what do you think endocrinology looks like in 10 years?
in a first, someone bought a bulk order of 500 copies of my children's book about clinical trials
I made this book during peak COVID despair, basically because I just thought the sentence "if you give a mouse metformin was funny"
since then it's been funny how it's taken on a life of it's own
- People have written very serious reviews on Amazon reviewing the validity of the trial
- I get texts and videos all the time of people's kids trying to say the word "metformin"
- I've learned what children's book publishers care about and how Kindle Direct Publishing works
- I've read it to my own son who will say things like "father, why did they use surrogate endpoints instead of mortality?" (his first words"
Truly a sidequest of sidequests, but I'm still learning things from making it!

So uh, I wrote a children's book for adults about how clinical trials and drug development work
You should buy a copy here
amazon.com/dp/B08CWM8QZW?ref…

We're working with a few really interesting healthcare companies to help them hire the following roles - below are the most common roles we're getting asked:
1. AI / forward-deployed engineers
Companies want builders who can ship AI products and turn messy customer workflows into working software. Hands-on experience with LLM tooling, evals and integrations keeps coming up.
2. Operators who build from scratch
First ops hires, chiefs of staff and bizops leads who can create processes, own cross-functional execution and automate manual work. Healthcare operations experience is valuable for the roles closest to care delivery.
3. Sales and growth leads
People who can own pipeline or customer acquisition end to end, rather than just manage a slice of it. The recurring ask is hands-on selling and experimentation, with an understanding of how healthcare buyers make decisions.
if you know someone that's excellent (you would personally vouch for them) and thinking about their next thing, you should send them our way
The jump to starting a company can feel massive - especially when you have bills to pay.
Often founders raise venture early mostly just to ease the anxiety of having money. I do remember thinking to myself…”should I just raise???” when looking at my bank account slowly draining.
I have always wished there was more capital available that just gave people more freedom to explore ideas without that pressure. This is especially true as the cost of experimenting has now gone down dramatically thanks to AI.
Very excited to work with the Deerfield Management team to do that, giving $10K non-dilutive grants to selected teams to explore ideas at our upcoming hackathon + the chance to win up to $120K more and additional credits from companies we’re partnering with.
You should have the space to experiment with ideas first, and figure out how to capitalize your company second.

I gotta start charging for the newsletter, I get like 1 text every few weeks after the hospital indemnity insurance post

2
10
2,306
I liked this idea around letting patients directly shop for value-based care and maybe participate in the upside
The idea: A portal to look up all the different entities that a patient is “attributed” to: what ACO or health plan you’re in, if you’re in a risk contract, if you’re enrolled in ACCESS, etc. The idea is that you put in your patient info and authorize it to reach out to PCPs, insurers and CMS on your behalf.
In theory it lets consumers partner on “value based” contracts, and ultimately it can be a vector for joint savings with the consumer directly, similar to how car insurance gives bonuses if you don’t speed.
As a patient, how do I proactively decide which provider I should see in primary care and non-hospital specialty settings? And how do I decide which orgs should be managing my health long term (insurer, ACO, PCP, health system or ACCESS org)? With info on which orgs are accountable for your health, plus info on the alternatives, you can “shop”.
Value-based care is broadly the right idea, but outside of some quality metrics on health plans there are basically no tools for patients to measure any of it. US health consumers actually have some sophistication and can understand the idea of preventive and population health. The reality is that also many parts of the care you get are going to be influenced by the type of payment arrangement your doc is in.
It’s a great play for managed care orgs that believe they can reduce spend and improve outcomes, because it gives them a way to pass savings directly on to customers, a la the car insurance example. Part of the problem in healthcare is that it’s so difficult to understand which entity actually benefits from prevention, so this helps show the dollar flow and could incentivize patient behavior.
You can prob build it today:
1) One big point of friction is the willingness to sit on the phone with insurers and providers to get an answer. Solved by AI agents.
2) Another is the willingness to wade through CMS and NCQA PDFs on ACO performance. Also solved with LLMs.
3) No full solve for insurer-to-ACO contracts in the private market, but you can probably find some of this out for Medicare/Medicaid I think.
If you can actually get this working, there are a lot of ways to make money. The easiest is D2C advertising or consulting (oh look, your ACO or insurer sucks, good news, open enrollment is coming up and you can choose plan, ACO or provider X). More complex ones are around using data and patient behavior changes to share savings. HSAs sort of try to do this, but there are so few levers there.

5
14
1,708
I think people in the US really want an egalitarian healthcare system where you can’t pay for better care if you have more money.
So instead getting access to better care still happens much more subtly. Getting better insurance at a high paying job, “knowing someone” to get quicker access to a specialist, etc.
7
22
4,141